
Published
Choose a surgeon who regularly treats your kind of hand or wrist problem and can explain what you might gain from surgery, another treatment, or waiting. Start with a task you want to get back: buttoning a shirt, holding a steering wheel, or sleeping without waking up to a numb hand. That gives you and the surgeon a way to judge whether a treatment is worth its risks and recovery time. Seeing a hand surgeon does not commit you to an operation. [1]
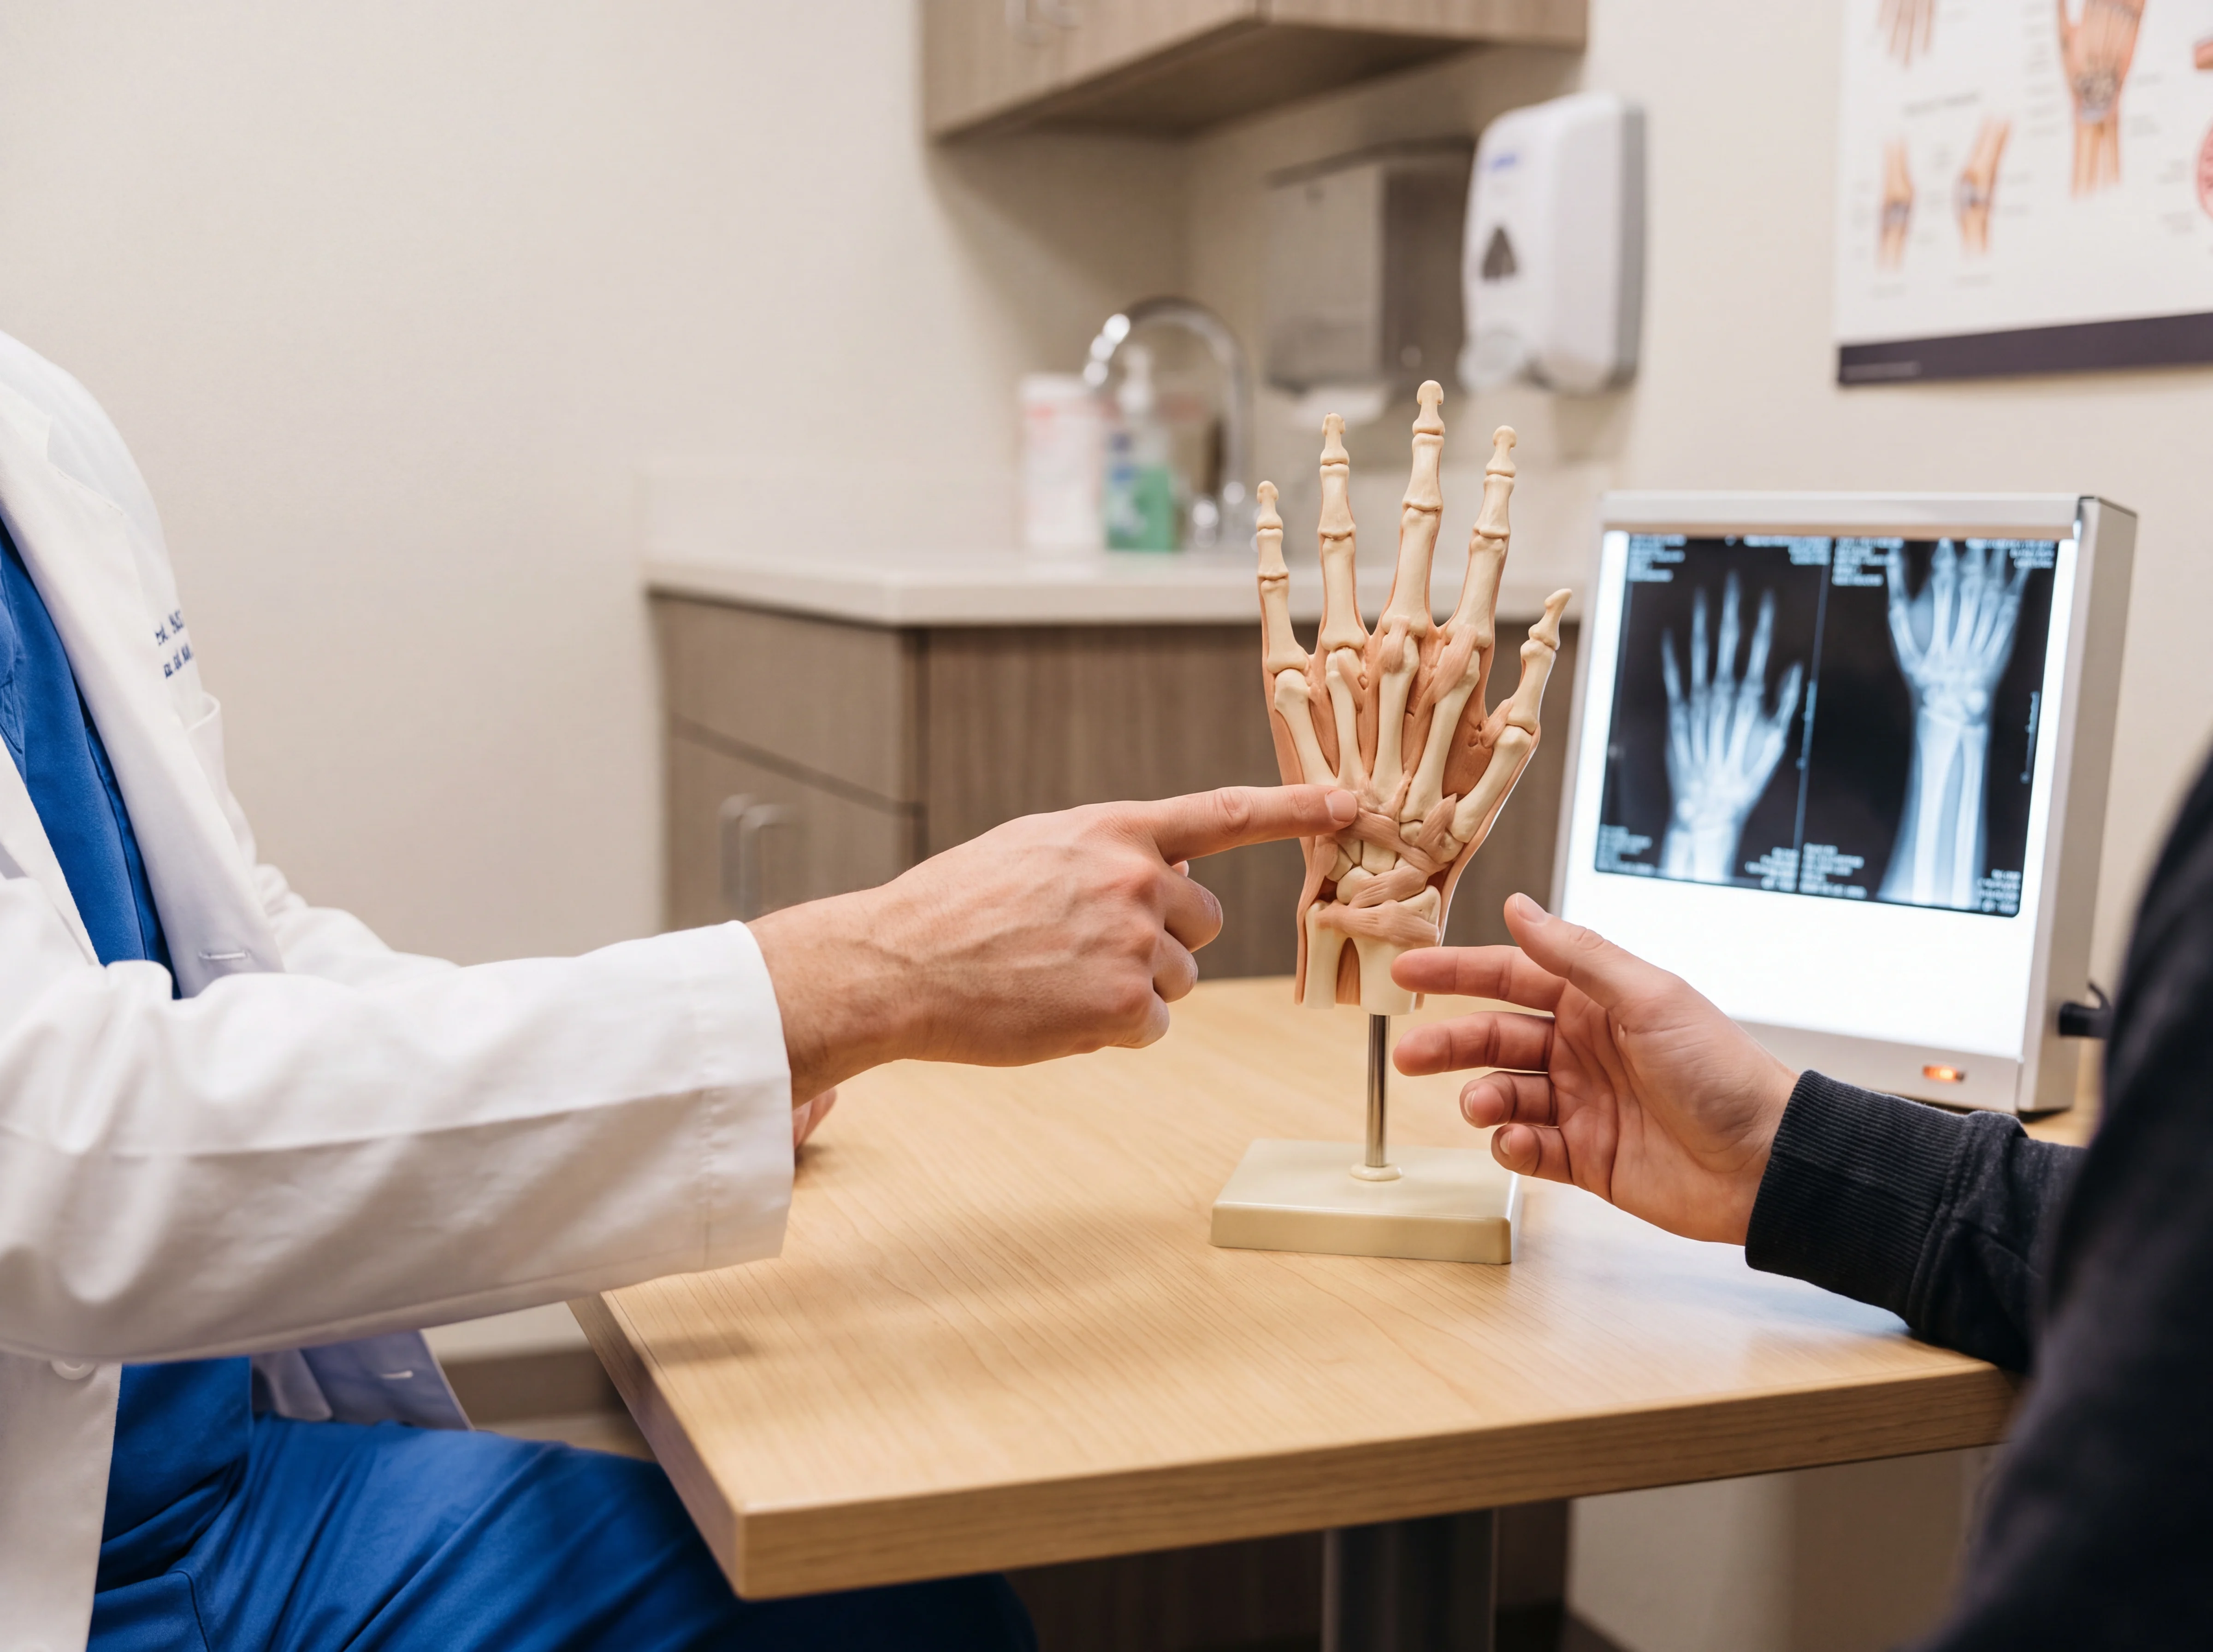
- 1Hand and wrist teaching model used to explain anatomy.
- 2Patient and clinician discuss which movement or symptom matters most.
- 3Imaging can help answer a specific question when it fits the examination.
Some injuries should not wait for a routine appointment. If you cut a finger and can no longer bend it, seek prompt medical assessment even if the cut looks small. A tendon that bends the finger may be injured. If the finger is cold and pale after the injury, seek emergency care; its blood supply may be affected. [2]
Check the surgeon’s credentials
Our physician directory includes several specialties. Use it to find names, then read the profiles. An area of practice is not a credential. When you call, describe your diagnosis or symptoms so the office can help you decide whether to book a visit. [3]
Check the physician’s California license through the Medical Board of California. Its verification page also directs you to the osteopathic board for a physician with a D.O. degree. A license establishes permission to practice, not training in hand surgery. [4]
Hand surgeons may start in orthopedic, plastic, or general surgery. A hand fellowship is focused training after residency. Board certification is a separate qualification: ask which board awarded it and in what specialty. [1] For an orthopedic surgeon, a subspecialty certificate in surgery of the hand involves additional training, a review of surgical cases, and an exam. It is one useful credential, not a requirement for every surgeon who treats hand problems. [5] You can check American Board of Medical Specialties credentials through Certification Matters. [6]
Questions about credentials and experience
- What training did you complete specifically in hand and wrist care, and which board certifications do you hold?
- How often do you treat people with my problem, including people who have already tried the treatments I have?
Compare treatments for your diagnosis
Bring any imaging reports and a list of treatments you have tried. If you have had surgery on that hand, bring the operation report if available. Describe what changed after treatment and what still gets in your way. The next decision may be different if a treatment never helped than if it helped for a year.
Consider carpal tunnel treatment options as an example. In carpal tunnel syndrome, a nerve is squeezed at the wrist. A corticosteroid injection can improve symptoms in the short term, but the 2024 American Academy of Orthopaedic Surgeons guideline found no long-term benefit. An operation releases a ligament to give the nerve more room. If endoscopic release is proposed, ask why: patients report similar long-term outcomes with endoscopic and small open releases. That does not mean every risk is the same. [7]
In a Dutch trial of 934 adults who had symptoms for at least six weeks and a diagnosis confirmed by nerve testing or ultrasound, researchers compared starting with surgery against starting with an injection. At 18 months, 61% of those assessed in the surgery group and 45% in the injection group scored in the recovered range on a symptom questionnaire. People in either group could have more treatment. Those results describe two starting strategies, not your personal chance of recovery after one procedure. [8]
Questions about the choice
- Can you show me what is causing my symptoms and explain whether another test would change the plan?
- What might improve with a brace, therapy, an injection, or time—and what might I lose by waiting?
- If you recommend surgery, how often do you perform this operation, what could go wrong, and who would manage a complication?
- How much time can I safely take to get a second opinion?
Compare the setting, anesthesia, and cost
For outpatient surgery, the plan is to go home the same day. Your health, the operation, and the help available at home belong in that decision. Our patient forms include a disclosure about physician ownership and your choice of facility. Our facility fee is separate from the surgeon’s and anesthesiologist’s fees. [9] Use our insurance and billing guide to prepare for a call with your insurer.
Questions before scheduling
- Why is this facility appropriate for me, are you approved to perform this operation there, and what happens if I need hospital care?
- Will I be awake with the area numbed, have a nerve block, receive sedation, or need general anesthesia—and what should I expect to feel?
- Who will bill me, who is in my insurance network, and does my estimate include a brace, follow-up visits, or hand therapy?
Make a medicine plan as soon as surgery is considered
Share a full medicine list, including blood thinners, insulin, nonprescription medicines, and supplements. If you take an SGLT2 inhibitor, such as empagliflozin or dapagliflozin, flag it when scheduling—even if you take it for heart or kidney disease rather than diabetes. These medicines generally need a planned pause several days before elective surgery. Around surgery, they can contribute to ketoacidosis, a dangerous acid buildup that can occur even when blood sugar is not very high. Get instructions from your team rather than changing a dose yourself. [10]
Mention GLP-1 medicines or related drugs, such as semaglutide or tirzepatide, whether you take them for diabetes or weight loss. They can slow stomach emptying, which matters because stomach contents can enter the lungs during general anesthesia or deep sedation. Tell the team your dose, your last dose, any recent increase, and whether you have nausea or vomiting. Ask for one plan that accounts for anesthesia safety and blood sugar. [10]
Questions about preparation and medicines
- Who will coordinate with my prescriber and give me written instructions for eating, drinking, and taking or restarting each medicine?
- If I have diabetes, how should I check my glucose while fasting, what supplies should I bring, and whom should I call for a low or high reading?
- If my instructions disagree, or I feel sick before surgery, which team member should I call before I come in?
Plan the ride home and the first days of recovery
Our surgery preparation guide asks you to arrange for someone to bring you, escort you home, and plan to stay with you for 24 hours. Tell the team before surgery if that will be difficult. [11] Think through an ordinary morning with one hand limited: opening a medicine bottle, getting dressed, or fastening a child’s car seat. Your companion can help plan for those tasks and listen to the discharge instructions with you.
Questions for you and your companion
- What should my companion help with, especially while my hand is numb?
- Which joints may I move, what must stay protected, and when will we decide whether I need hand therapy?
- What must I be able to do before I can drive, type, lift, or use tools safely?
- Which changes need an immediate call, which mean going to the emergency department, and what number works after hours?
With a cast or splint, call the surgical team right away for increasing pain with tightness, unexpected numbness or tingling, or marked swelling beyond the dressing. Loss of the ability to move fingers that were free to move needs urgent evaluation. Do not wait for the next appointment. [12]
This article is for education, not a diagnosis or an individual treatment plan. Follow your surgical team’s instructions. Call 911 for chest pain or trouble breathing.
Learn More
- What Is a Hand Surgeon?
- Flexor Tendon Injuries
- Surgery Center of Long Beach: Physicians
- Medical Board of California: License Verification
- American Board of Orthopaedic Surgery: Surgery of the Hand
- American Board of Medical Specialties: Certification Matters update
- Management of Carpal Tunnel Syndrome: Evidence-Based Clinical Practice Guideline
- Surgery versus corticosteroid injection for carpal tunnel syndrome (DISTRICTS): an open-label, multicentre, randomised controlled trial
- Surgery Center of Long Beach: Multiple Authorization Form
- Diabetes Care in the Hospital: Standards of Care in Diabetes—2026
- Surgery Center of Long Beach: How to Prepare for Surgery
- Care of Casts and Splints
Sources checked November 22, 2026.