
Published
Ask about knee replacement when knee pain or stiffness regularly limits your life and the treatments you can safely use no longer help enough. That might mean you wake up in pain, need someone else to do the shopping, or can no longer stand long enough to cook dinner. An X-ray helps show what is damaged. It cannot tell you how much those losses matter to you. Meeting with a surgeon is a way to weigh your options, not a promise to have surgery. [1] [2]
Start with what you want to do again
Before your appointment, finish this sentence: “If my knee felt better, I would like to ___.” Be specific. “Walk my granddaughter to school and get back home” tells the surgeon more than “walk farther.” Include what stops you now. Does pain make you turn back? Is it hard to bend the knee enough to step off a curb? Does the walk go well, but the pain keep you awake that night? These details help connect the examination to the problem you want treated. [1] [2]
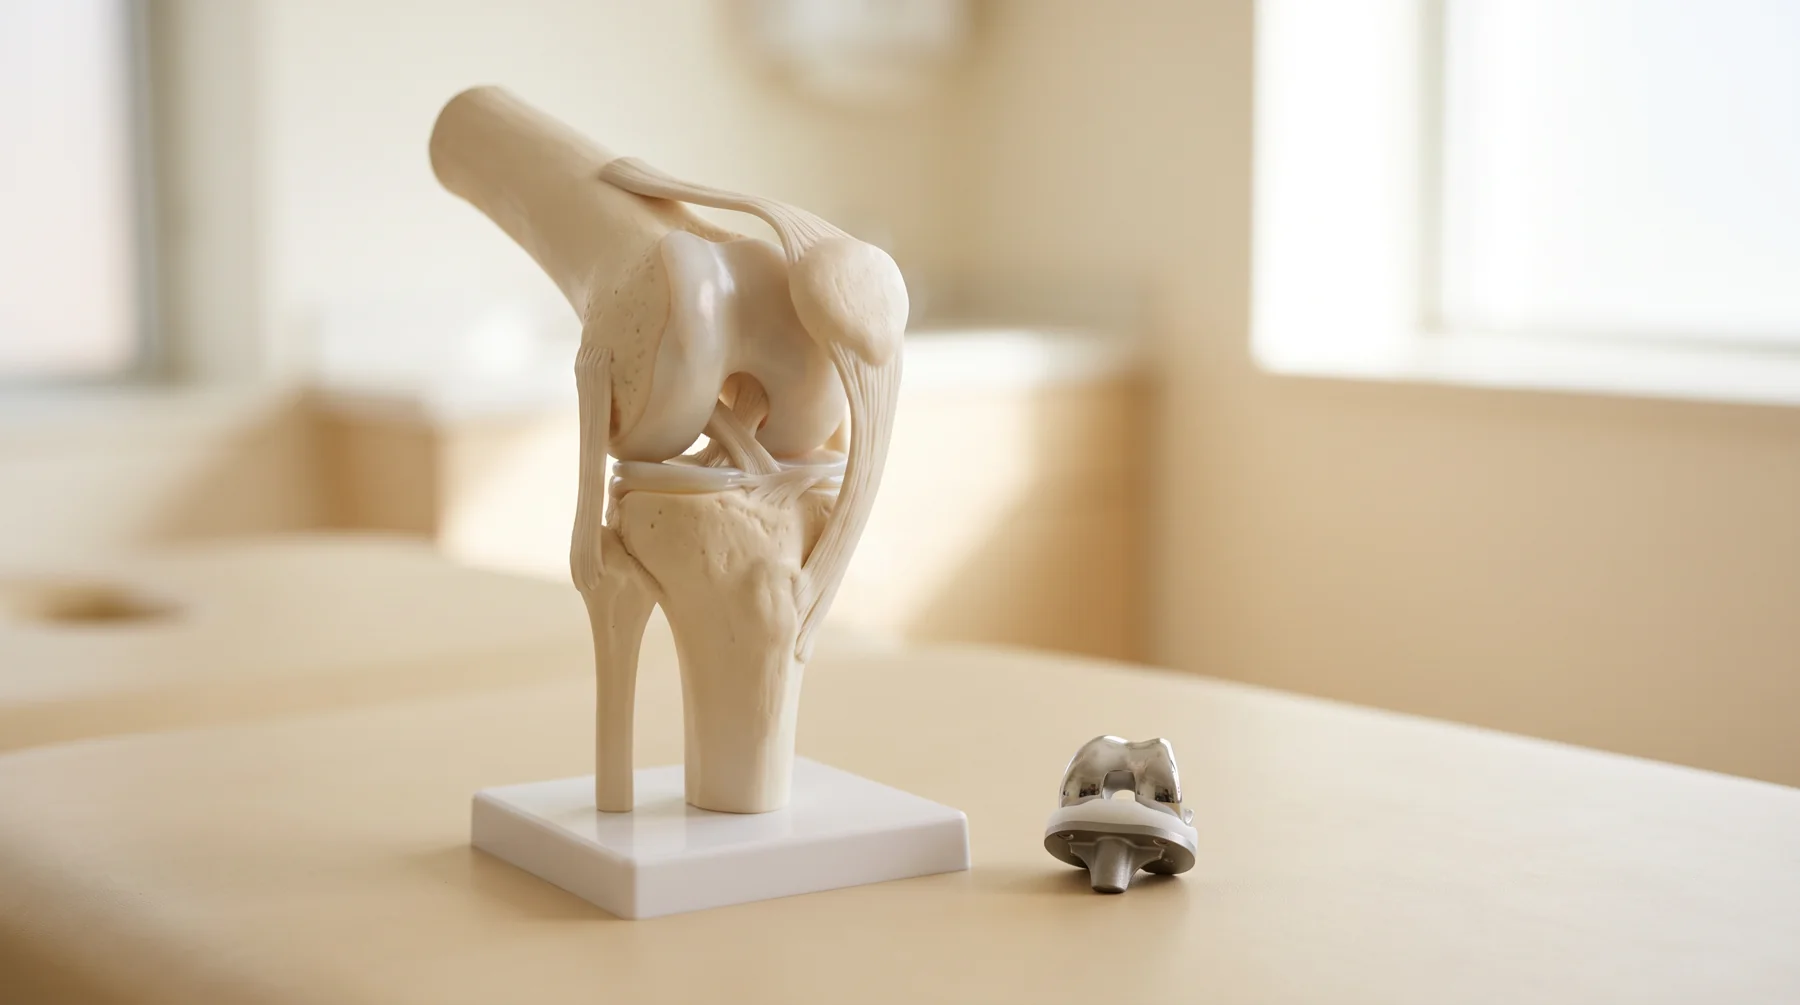
- 1Thighbone (femur), above the knee joint.
- 2Shinbone (tibia), below the knee joint.
- 3Kneecap (patella), in front of the joint.
- 4Separate sample implant component; the actual choice is individual.
In osteoarthritis, the smooth covering on the ends of the bones wears down. Arthritis can also follow a knee injury. The surgeon will ask about your symptoms, check how the knee moves and how steady it is, and look at X-rays to see where there is damage. Ask the surgeon to show you which finding best explains your difficulty. Then ask what is likely to improve and what might not. Walking is a realistic goal for many people after replacement. Comfortable kneeling and a full bend are less certain. [2]
Some leg symptoms should not wait for a knee appointment. Pain that travels from the back down the leg can come from a nerve in the spine. Go to the emergency department now if you develop new trouble passing urine, lose control of your bladder or bowels, or notice new numbness between your legs, around your genitals or around your bottom. Any new weakness in a leg or foot needs same-day medical assessment. If the weakness is severe or getting worse quickly, go to the emergency department now. [3]
What can help before surgery?
Exercise should fit what you can do now. The American College of Rheumatology’s board-approved 2026 summary recommends exercise for knee osteoarthritis. A physical therapist can help you choose a starting point, such as exercises to strengthen your legs or a form of exercise you can keep doing when a long walk is too painful. If balance or pain limits walking, ask whether a cane would help and how to use it. Pick one everyday task to track so you can tell whether the plan is helping. [1] [4]
| Option to discuss | What it may help with | A practical question |
|---|---|---|
| Strength and fitness exercises | Less pain and more ability to do daily tasks with regular practice. [1] [4] | “How could I change this exercise if it keeps me from doing the rest of my day?” |
| Anti-inflammatory gel or pills | A gel applied to the knee can ease pain. Pills are another option, but stomach bleeding, kidney or heart problems, and other medicines affect whether they are safe. [1] [4] | “Can you check this against everything I take, including nonprescription medicines?” |
| Steroid injection into the knee | It may ease pain for a short time, sometimes enough to make exercise easier. If replacement is under discussion, the date of an injection matters for planning surgery. [1] [5] | “Would an injection help with my goal now, and could it affect the timing of surgery?” |
| Weight-loss support, if relevant to you | For people with overweight or obesity, weight loss can ease knee pain and make movement easier. For knee arthritis with obesity, a prescription weight-loss medicine may be an option alongside changes in eating and activity. [1] [4] | “What support fits my health, and what can we do for my knee in the meantime?” |
You do not have to keep repeating a treatment that has not helped enough. A US timing guideline addresses a specific group: people with moderate-to-severe symptoms and joint damage on X-rays who have tried appropriate nonsurgical care and have decided with their surgeon to have a replacement. For them, the guideline advises against putting off surgery just to try more therapy, anti-inflammatory medicine or injections. The advice is conditional: the evidence is limited, and people may reasonably make different choices. It is not a reason to rush if your current plan works. [5]
How much difference might total replacement make?
A Danish study compared having surgery first with starting a treatment program and keeping surgery as an option. It included 100 adults considered eligible for replacement of one knee. They were randomized, meaning chance decided which plan each person started with. Both groups were offered 12 weeks of exercise, education about arthritis, dietary advice, shoe inserts and pain medicine. The surgery-first group also had a total knee replacement. [6]
| What the researchers measured | Surgery first | Program first |
|---|---|---|
| Average improvement at one year on a 100-point knee score | 32.5 points | 16 points |
| Serious medical events recorded during that year | 24 events | 6 events |
Both groups improved; the surgery-first group improved more on average. The score combined pain, other knee symptoms, daily activities and knee-related quality of life. The points are not percentages of patients who got better. The second row counts events, not people: one person could have more than one event, and the study did not establish that treatment caused every event. [6] [7]
Starting with the program did not close the door on surgery. Of the 50 people who started that way, 13 had a replacement by one year and 16 by two years. That means 34 had gone two years without replacement, not that they would never need one. At two years, the group assigned to surgery first still had the larger average gain. [6] [8]
How well do those results fit you? A Cochrane review that searched from 2010 through January 2025 found just one trial that met its rules: the Danish study. The reviewers judged that the extra pain relief from surgery might be large enough to notice. The extra gain in daily function might not be. The added risk of serious harm was very uncertain. Surgeons’ rules for selecting patients were not clear, 12% of participants had mild arthritis on X-rays, and people with severe pain in the previous week were excluded. [7]
There is also a difference between less pain and no pain. A separate review estimated that about 13 in 100 people had a poor pain result one year after total knee replacement. The likely range for that average was about 10 to 16 in 100. Some studies counted ongoing moderate or severe pain; others counted pain that did not improve enough. Not everyone was available for follow-up. The result does not mean the other 87 were pain-free. [9]
Partial or total: what is the difference?
We offer total knee replacement as part of our orthopedic care. Your surgeon can explain whether a partial or total replacement fits your knee and confirm where your operation would take place. [10]
The knee has three main areas: the inner side, the outer side, and the surface where the kneecap meets the thighbone. A partial replacement resurfaces one damaged area and leaves the healthy areas in place. It may be an option when advanced arthritis is confined to one area. How well the knee bends and whether its supporting ligaments are sound also matter. Recovery can be quicker, but arthritis can later develop in the parts left untouched. [11]
A total replacement treats a broader area and may fit better when damage is widespread. “Total” does not mean the whole knee is removed. The surgeon shapes the worn ends of the thighbone and shinbone, covers them with metal parts, and places a durable plastic surface between them so they can glide. The underside of the kneecap may also be resurfaced. Ask to see the areas that would be replaced on your own X-rays. [2] [11]
For someone who qualifies for either operation, it helps to separate two questions: How might my knee feel? and How likely am I to need another operation? In the UK TOPKAT trial, 528 people with advanced arthritis on the inner side of the knee were assigned to partial or total replacement. At ten years, average pain and function scores were similar. About 5 in 100 in each group had a revision, an operation to change implant parts. Many participants did not complete the ten-year questionnaire. The similar revision counts do not prove the risks are identical. [12]
A larger study looked at a registry: records of operations done in everyday practice. Researchers used the National Joint Registry for England, Wales, Northern Ireland and the Isle of Man and matched 54,215 partial replacements with the same number of total replacements. Here is what they found. [13]
| In the registry study | Partial replacement | Total replacement |
|---|---|---|
| Revision by ten years | 12 in 100 | 5 in 100 |
| Any further operation on that knee by ten years, including revision | 25 in 100 | 21 in 100 |
| Death from any cause by ten years | 13.6% | 15.5% |
Early complications were less frequent after partial replacement in the registry, but later knee operations were more frequent. Unlike the trial, the registry did not assign operations by chance. Differences in health, in who was offered each operation, or in surgical experience may matter. The figures do not show that choosing a partial knee makes someone live longer. If either operation fits your knee, ask how often your surgeon performs each and which tradeoff matters for you. [12] [13]
What might change the timing or the place of surgery?
Replacement carries risks, including infection, blood clots, stiffness and lasting pain. An infection deep around the implant can require another operation. Over time, parts can wear or loosen. Ask which risks are most relevant to your health rather than relying only on an average for everyone who has surgery. [2] [5]
Waiting to make an operation safer is different from waiting to try another arthritis treatment. The US timing guideline supports considering a delay to improve poorly controlled blood sugar or to reduce or stop nicotine use. Higher body weight can raise surgical risks, but the guideline advises against delaying an otherwise appropriate replacement solely to reach a rigid weight target. Ask, “What risk are we trying to reduce, and when will we look at it again?” Ask our team how these recommendations apply to your health and surgical plan. [5]
Being a candidate for surgery does not automatically make you a candidate to go home that day. The American Association of Hip and Knee Surgeons advises weighing the need for medical monitoring, the complexity of the operation and the help available at home. Tell the team if you live alone, if there is no handrail on your steps, or if the only bathroom is on a different floor from your bed. Ask whether an outpatient setting or a hospital would be safer for you before making arrangements. [14]
Prepare for the first evening
Bring your actual medicine list. Include prescriptions, medicines you buy yourself, vitamins and supplements. Tell the team about allergies, past problems with anesthesia, diabetes, heart or lung conditions and any previous blood clot. Get written instructions about eating, drinking and medicines. If you use a blood thinner or diabetes medicine, make sure the clinician who prescribes it and the surgical team agree on the plan. Do not stop or restart it based on general advice. [14] [15] [16]
Ask what you will feel during and after the operation. General anesthesia makes you unconscious. A spinal anesthetic numbs the lower body; you may also receive medicine to make you sleepy. A nerve block numbs part of the leg and can help with pain after surgery. If a previous anesthetic made you very sick to your stomach, mention it. Ask what to expect as feeling returns and when it will be safe to stand with help. [16]
Picture arriving home with your hands on a walker. Who will unlock the door, carry your things and help with dinner? Clear a path to a sturdy chair and the bathroom. Move loose rugs and put frequently used items within reach. Arrange a ride and decide who can help with meals, pets or anyone who depends on you. If that help is not available, say so while the team can still take it into account. [14] [15]
Before leaving, ask to practice getting up, using your walking aid and managing any steps you cannot avoid. You and your helper should know how much weight you may put on the leg, how to care for the dressing, when you may shower, and what your plan says about pain and clot prevention. Write down whom to contact with questions, including outside usual office hours. Ask who will arrange therapy or a home visit if one is recommended. [14] [15] [17]
Measure recovery by what you can safely do
At first, progress may mean getting to the bathroom safely or standing up from a chair without losing your balance. Later, it may mean straightening the knee more easily, walking farther or using stairs with confidence. The 2026 physical therapy guideline recommends supervised therapy after total knee replacement. Our joint replacement recovery guide can help you prepare questions for that plan. Where it takes place should depend on your safety, walking ability and living situation. Ask who will check your progress and how to get exercises adjusted if pain or swelling keeps you from doing them. [15] [17]
Use the same approach for work and driving. Tell the team what a shift actually involves: sitting at a desk, standing at a counter and climbing a ladder are different tasks. Before driving, you need enough bend to sit comfortably and enough control to brake promptly. Do not drive while taking medicine that impairs alertness. Ask your team when it is safe for you, rather than using someone else’s return date. [2] [15]
After surgery: symptoms that should not wait
- Call 911 for possible signs of a clot in the lung: new trouble breathing, chest pain, coughing up blood, an unexplained fast or irregular heartbeat, or sudden lightheadedness or fainting. Chest pain may get worse with a deep breath or cough. You do not need to have leg symptoms first. [15] [18]
- Get urgent same-day medical assessment for a possible clot in either leg. Look for new or worsening swelling, pain, tenderness, warmth, redness or another color change. Symptoms can involve the thigh, calf, ankle or foot. Some swelling is expected after surgery, but do not dismiss a new change, swelling beyond what your team described, or symptoms in the other leg. [2] [15] [18]
- Contact your surgical team promptly for fever or chills, spreading redness or darkening around the incision, an opening in the wound, new or increasing drainage, or knee pain that is getting worse instead of easing. Heavy bleeding from the surgical area is an emergency: call 911. [2] [15]
Questions to ask your physician
You do not need to ask every question in one visit. Bring the ones that fit your health, goals, and home situation. If a friend or family member will help you, invite them to hear the plan with you.
Choosing a treatment
- Can you show me on my X-rays which parts of the knee are damaged, and explain which symptoms a replacement is likely to improve or leave unchanged?
- Which nonsurgical treatments still fit my goals? If I wait, what change in pain, function, or the joint would make us reconsider surgery?
- Are total and partial replacement both reasonable for my knee? Which operation would you recommend, and why? Is that the exact operation you would perform here?
- What are the main risks in my case, including infection, clots, lasting pain, stiffness, or another operation? How do my other conditions change those risks?
Getting ready
- What tests or visits do I need before surgery, and who will coordinate my surgeon, anesthesia team, primary care clinician, and any specialists?
- Please review my complete medication list, including blood thinners, diabetes drugs, insulin, GLP-1 medicines, pain medicine, vitamins, and supplements. Who will give me written instructions about each one, and whom should I call if instructions conflict?
- If I have diabetes, heart or lung disease, sleep apnea, a prior clot, or another condition, what should be stabilized or monitored before deciding on a same-day operation?
- Which anesthesia and pain-control options might fit me? What should I tell the anesthesia team about prior reactions, nausea, or medicines I take?
- Would my health and the help available at home make care here or in a hospital safer for me? Who makes that decision, and when?
- What costs should I confirm with my insurer and our team, including the surgeon, anesthesia, implant, therapy, equipment, and any unexpected hospital care?
Going home and recovering
- Who should drive me home and stay with me, and for how long? What should my companion learn about walking, steps, medicines, and warning signs before we leave?
- What walking aid, home changes, therapy, and clot-prevention plan will I need? Who will arrange them and check that they are in place?
- How much weight may I put on the leg? How do I care for the dressing, and when can I shower, drive, work, travel, and return to the activity I named as my goal?
- Which symptoms mean call 911, seek same-day assessment, or call your office? What is the after-hours number, and who changes the plan if pain or swelling prevents progress?
You can leave the visit with a surgery date, a plan to keep treating the knee without surgery, or a question you want answered first. A useful decision is one you can explain in your own words: what you hope to gain, what risks you are willing to take, and what you will do next.
Learn More
- National Institute for Health and Care Excellence. Osteoarthritis in over 16s: diagnosis and management. NG226, 2022. Sections 1.3–1.6
- American Academy of Orthopaedic Surgeons (AAOS). Total Knee Replacement. OrthoInfo
- Burger ST. Back Pain. Textbook of Urgent Care Medicine, chapter 40. Journal of Urgent Care Medicine, 2026. See Table 1
- American College of Rheumatology. 2026 Update of the Recommendations for the Management of Osteoarthritis of the Knee, Hip, and Hand. Board-approved summary
- Hannon CP, et al. 2023 ACR/AAHKS clinical practice guideline for the optimal timing of elective hip or knee arthroplasty. Arthritis Care & Research. 2023;75:2227–2238
- Skou ST, et al. A randomized, controlled trial of total knee replacement. New England Journal of Medicine. 2015;373:1597–1606
- Pacheco-Brousseau L, et al. Total and partial knee arthroplasty versus non-surgical interventions of the knee for moderate to severe osteoarthritis. Cochrane Database of Systematic Reviews. 2026;CD015378
- Skou ST, et al. Total knee replacement and non-surgical treatment of knee osteoarthritis: 2-year outcome from two parallel randomized controlled trials. Osteoarthritis and Cartilage. 2018;26:1170–1180
- Cheng H-Y, et al. What proportion of people have long-term pain after total hip or knee replacement? An update of a systematic review and meta-analysis. BMJ Open. 2025;15:e088975
- Surgery Center of Long Beach. Specialties: Orthopedic Health Procedures
- AAOS. Unicompartmental (Partial) Knee Replacement. OrthoInfo
- Beard DJ, et al.; TOPKAT Study Group. Assessing clinical and cost effectiveness of total versus partial knee replacement: 10-year follow-up of a multicentre, randomised controlled trial. Lancet Rheumatology. 2026;8:e116–e126
- Mohammad HR, Liddle AD, Judge A, Murray DW. A matched comparison of long-term outcomes of total and unicompartmental knee replacements in different ages based on national databases. Journal of Arthroplasty. 2022;37:243–251
- American Association of Hip and Knee Surgeons. Outpatient Joint Replacement. Position statement, 2024 update
- Mayo Clinic. Total Knee Replacement Surgery. Patient education booklet MC2111. See preparation, recovery and “When to get medical care after total knee replacement.”
- AAOS. Anesthesia for Hip and Knee Surgery. OrthoInfo
- Bove AM, et al. Clinical practice guideline for physical therapist management of total knee arthroplasty: revision 2026. Physical Therapy. 2026;106:pzag058
- Centers for Disease Control and Prevention. About Venous Thromboembolism (Blood Clots)
Sources checked November 21, 2026.